Understanding Drf Crefito: Clinical Use and Top Practice
This guide explains how “Drf Crefito” and “Crefito” concepts are applied in clinical practice, emphasizing diagnostic reasoning, documentation quality, and patient safety. Objectively, these terms relate to joint-related auditory or tactile findings and how clinicians record them. The article then offers a structured comparison framework and practical decision steps.
Key takeaways on Drf Crefito and Crefito assessment
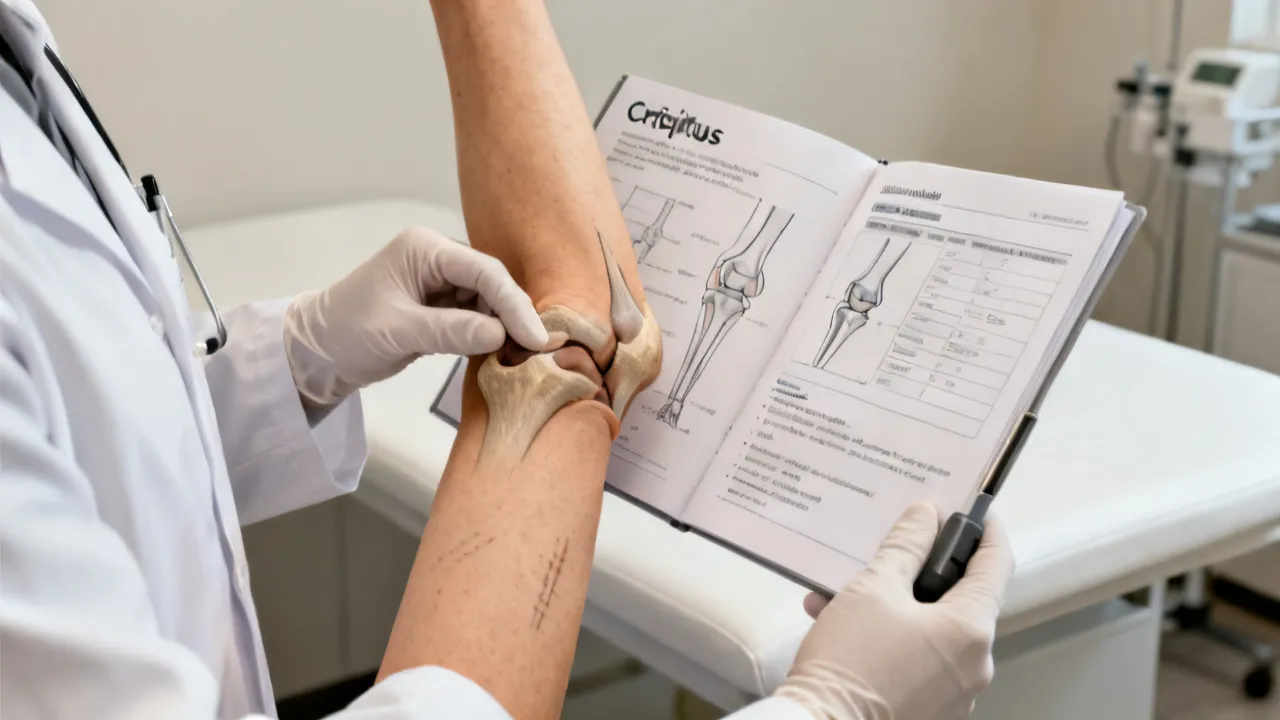
Drf Crefito is discussed here as a practical framework for how clinicians interpret and document crepitus (Crefito)—commonly described as joint “grinding,” “crackling,” or tactile-auditory phenomena—within an evidence-based assessment workflow. The goal is to support consistent examinations, reduce diagnostic ambiguity, and improve communication across care teams through clear criteria, standardized notes, and appropriate follow-up.
What the terms typically refer to in real-world clinical reasoning
In many clinical contexts, Crefito is used to denote crepitus, a phenomenon patients may describe as cracking or grinding, and clinicians may detect during movement through both listening and palpation. Although the exact spelling can vary by language, the underlying clinical idea is consistent: movement of joints can produce audible or tactile signals, which may correlate with degenerative changes, altered mechanics, inflammation, or other musculoskeletal conditions.
Drf Crefito commonly appears as a shorthand used in care settings to structure assessment documentation and decision-making around those findings. From an expert perspective, the value is less about the label itself and more about the method: capturing when the phenomenon occurs, how it behaves across range of motion, what it accompanies (pain, stiffness, swelling, instability), and whether it aligns with likely clinical hypotheses.
Why clinicians focus on documentation—not just the sound
Experienced clinicians rarely treat crepitus as a standalone diagnosis. Instead, they consider it one data point among many. In practice, Drf Crefito approaches tend to emphasize that the very clinically actionable information includes:
- Location: which joint segment (e.g., patellofemoral area, elbow compartment, shoulder region) produces the phenomenon.
- Timing during motion: early, mid, or end range.
- Reproducibility: whether the finding is consistent across repetitions.
- Associated symptoms: pain intensity, stiffness duration, swelling, locking, or instability sensations.
- Functional impact: how it affects activities of daily living and movement quality.
- Risk context: patient age, prior injury, occupation or sport biomechanics, and comorbidities.
That broader lens improves decision quality—especially when patients present with complaints that can overlap across conditions such as osteoarthritis, tendinopathies, meniscal issues, bursitis, or post-traumatic irregularities.
When crepitus is very clinically meaningful
Crepitus becomes more meaningful when it is accompanied by other findings. In expert practice, Crefito is interpreted through a triad:
- Symptoms: pain, morning stiffness, swelling, or functional limitation.
- Physical findings: tenderness, reduced range of motion, effusion, instability tests, or altered tracking.
- Mechanistic coherence: whether the phenomenon fits the suspected anatomy and movement pattern.
For example, a patient who reports crepitus without pain may not require the same immediacy as someone with painful crepitus plus restricted movement or night pain. The clinician’s job is to assess probability and urgency rather than rely on the phenomenon alone.
Structured clinical workflow aligned with Drf Crefito principles
A practical Drf Crefito-style workflow can be summarized as “observe, quantify, correlate, and plan.” The objective is to produce a record that another clinician can interpret without needing to guess what you saw.
Observe: Note whether the phenomenon is audible, tactile, or both; identify the joint and side; document whether it occurs with specific movements (flexion/extension, rotation, weight-bearing, overhead activity).
Quantify: Describe intensity using a consistent scale in your facility (even a simple ordinal description such as “mild/moderate/severe” can be more helpful than vague wording). Record range of motion and whether crepitus appears before pain or after.
Correlate: Link findings to symptoms and functional impact. Ask targeted questions (e.g., “Does it hurt during the same phase of motion each time?” “Any episodes of catching or locking?” “Is there swelling after activity?”).
Plan: Decide on conservative management versus further evaluation. Consider imaging only when it is likely to change management or clarify diagnosis—an approach consistent with evidence-based musculoskeletal practice.
Industry perspective: how variability in terms affects care
One challenge in real-world documentation is terminology variability. Drf Crefito may be recorded differently across clinics or regions, while Crefito may be used as a general label for crepitus. From an expert standpoint, the risk is that different notes may appear to mean the same thing while actually capturing different clinical realities.
To mitigate that, clinicians benefit from standardized narrative templates: even if the label varies, the content of the description remains stable—location, timing, pain association, and functional context. This is especially important for handoffs between primary care, physiotherapy, orthopedics, and radiology.
Comparison table: supplementing assessment choices (no links)
| Assessment element | Emphasis in Drf Crefito-style documentation | What to check when using Crefito wording |
|---|---|---|
| Core phenomenon | Describe tactile/audible crepitus, not only a label | Clarify whether “Crefito” denotes crepitus vs another sensation |
| Motion phase | Record early/mid/end range and movement direction | Identify whether it consistently appears at the same phase |
| Pain relationship | Document timing of pain relative to crepitus | Specify whether pain precedes, coincides, or follows crepitus |
| Reproducibility | Note consistency across repeated movements | Record if it changes with fatigue, activity, or posture |
| Associated signs | Include swelling, tenderness, stiffness, catching/locking | State which associated symptoms were present or absent |
| Clinical next step | Choose conservative pathway or targeted evaluation based on likelihood | Decide whether imaging or referral adds actionable information |
Conditions and requirements for safe clinical use
To keep Drf Crefito and Crefito-related documentation safe and clinically useful, the following conditions are recommended:
- Clinical context is mandatory: Do not interpret crepitus findings without symptoms and functional assessment.
- Consistency in recording: Use the same movement protocol across visits when possible.
- Patient communication: Explain that crepitus does not automatically imply severe disease, but may correlate with it depending on associated findings.
- Escalation criteria: If there are red flags (e.g., significant trauma, suspected infection, progressive neurologic symptoms), follow local emergency and referral protocols.
- Referral when indicated: Persistent dysfunction, worsening pain, or failure of conservative strategies may warrant specialist evaluation.
Step-by-step approach for clinicians and care teams
Below is a practical, step-by-step guide that aligns with expert documentation standards for crepitus assessment (including how Drf Crefito is often operationalized).
- Collect the patient story: onset, aggravating/relieving factors, and whether symptoms track with specific movements.
- Inspect and palpate: note swelling, tenderness points, alignment, and tissue texture changes.
- Move through a standardized range: observe and palpate simultaneously when appropriate, capturing where Crefito occurs.
- Record intensity and phase: use a consistent descriptive scale and indicate early/mid/end range.
- Assess pain linkage: document whether pain is present, and its timing relative to the phenomenon.
- Check functional effects: evaluate gait, sit-to-stand, overhead reach, or sport-specific mechanics, depending on the joint.
- Form a differential hypothesis: weigh degenerative vs inflammatory vs post-traumatic vs mechanical causes using the full exam.
- Choose a management plan: typically start conservative when appropriate; specify expected outcomes and timeframe.
- Set follow-up and reassess: compare whether crepitus characteristics and symptoms change together.
Expert guidance on conservative management decisions
For many musculoskeletal presentations where Crefito is observed, conservative care may be appropriate—especially when there is no evidence of emergent pathology. The clinician’s decision should be driven by symptom severity, function loss, and exam findings rather than the sound itself.
From an industry and practice-management perspective, high-quality conservative pathways often include:
- Targeted strengthening aligned with biomechanics (e.g., quadriceps and hip control for knee-related mechanics when relevant).
- Mobility work to address stiffness and movement quality.
- Activity modification to avoid provocative loading patterns temporarily.
- Education on joint mechanics and expectations for symptom variability.
- Therapeutic reassessment to determine whether progress is occurring and whether the differential needs adjustment.
It’s also important to document what conservative strategies were tried and the patient response, so Drf Crefito-style notes remain clinically actionable over time.
Sources used for objective background context
To keep discussion evidence-aligned, background perspectives in this guide are consistent with widely used clinical principles and guidance in musculoskeletal care. When referencing general standards (such as cautious imaging selection and comprehensive assessment), the approach reflects established positions in peer-reviewed and health-system guidance. For readers who want formal reference points, standard sources include:
- Osteoarthritis clinical guidance: Recommendations summarized in major guideline documents (e.g., from professional societies and public health bodies).
- Radiology and imaging stewardship: Evidence-based principles discouraging unnecessary imaging when it won’t alter management.
- Rehabilitation practice standards: Consensus that structured exercise and education improve function in many common joint disorders.
Note: If you share your region or intended clinical setting, I can suggest specific local guideline titles and the very relevant sections for crepitus-related assessment and documentation.
FAQs about Drf Crefito and Crefito
1) What does “Crefito” mean clinically?
“Crefito” is commonly used to describe crepitus—audible or palpable crackling/grinding sensations during joint movement. Clinically, it is very useful when linked to pain, range-of-motion changes, swelling, or functional limitation.
2) Is Drf Crefito a specific diagnosis?
In very care settings, Drf Crefito functions more like a documentation and assessment framework rather than a single diagnosis. It emphasizes how clinicians record crepitus characteristics and correlate them with symptoms and exam findings.
3) Does crepitus always indicate severe disease?
No. Crepitus can occur in a range of conditions and may also be present without serious pathology. Clinical significance depends on associated symptoms, exam results, and changes over time—not on the sound alone.
4) When should a clinician consider imaging for crepitus-related complaints?
Imaging is generally considered when results are likely to change management, when there are concerning features (e.g., significant trauma, suspected inflammatory disease, or progressive neurologic issues), or when symptoms persist despite appropriate conservative treatment. This aligns with imaging stewardship principles used across musculoskeletal care.
5) What should be recorded during an exam for top continuity?
A strong note should include: joint location, movement phase (early/mid/end range), whether crepitus is audible/tactile, pain timing relative to the phenomenon, range-of-motion metrics, and any associated signs such as tenderness, effusion, stiffness duration, or locking.
6) How can patients help clinicians during history-taking?
Patients can describe: when the crepitus occurs (during stairs, squatting, overhead reaching), whether it hurts, whether it is improving or worsening, and whether they feel catching or instability. Short, specific examples often improve diagnostic clarity.
7) Are there specific “red flags” related to joint complaints?
Yes. Seek urgent evaluation if there is severe trauma, fever with joint symptoms, rapidly progressive swelling, unexplained systemic symptoms, inability to bear weight in sudden onset cases, or signs suggesting infection or serious inflammatory conditions.
8) Can crepitus improve with rehabilitation?
Often, yes—when the underlying driver is addressed (for example, mechanical overload, muscle imbalance, or movement-control deficits). Rehabilitation plans should be individualized and reassessed based on symptom response and functional outcomes.
Conclusion: using Drf Crefito to improve clinical clarity
Properly applied, Drf Crefito and Crefito-related assessment practices can raise the quality of musculoskeletal care by turning a vague report (“it cracks”) into a clear clinical observation that supports better differential thinking and more consistent follow-up. The central principle is simple and objective: document crepitus as a measurable phenomenon, then interpret it in the full clinical picture.
If you tell me the target joint (knee, elbow, shoulder, or another region) and the intended audience (clinician, student, patient education, or clinic SOP), I can tailor the workflow, FAQs, and documentation template structure accordingly.
Expanded clinical use of Drf Crefito: from shorthand to actionable assessment
A key reason clinicians adopt frameworks like Drf Crefito is that joint crepitus often enters clinical conversations in an informal way—patients mention “crackling,” clinicians feel a vibration or hear a sound, and the episode is quickly categorized as “normal aging” or “cartilage wear” without further unpacking. While such assumptions may be sometimes correct, they often ignore the nuance that makes crepitus clinically actionable: the pattern of when it occurs and how it behaves with movement, pain, swelling, and functional tasks.
When documentation is inconsistent, two clinicians can examine the same patient and reach divergent impressions—not because one is less competent, but because they captured different aspects of the phenomenon. One might record “crepitus present” without specifying phase, side, or pain association. Another might record “tactile crepitus with knee extension, end range, with pain 4/10” and also note effusion or impaired tracking. A third clinician reading the notes later may interpret these as different clinical pictures. The “value” of Drf Crefito is not that it replaces clinical reasoning; rather, it encourages the documentation habits that preserve that reasoning for future decisions.
Operational definitions: separating crepitus from other sensations
Because terminology can vary, one of the first quality steps is to clarify what sensation is being described. Patients sometimes report “crackling,” “popping,” “snapping,” “clicking,” “grinding,” “bubbling,” or even “tightness with movement.” Clinicians then need to determine whether the sensation aligns with crepitus (audible/tactile irregularity related to movement of articular or periarticular structures), or whether it is more consistent with:
- Instability or subluxation-related popping: a sudden shift sensation that may be accompanied by “giving way.”
- Tendon snapping: a localized snap often linked to specific positions and may involve friction over bony prominences.
- Locking/catching from mechanical obstruction: where movement is momentarily impeded, frequently associated with meniscal pathology or loose bodies.
- Painful range-limiting stiffness: where the patient perceives creaking but the primary problem is reduced mobility due to inflammation or guarded motion.
This distinction matters because it changes the differential diagnosis and the urgency of workup. A structured Drf Crefito note should therefore not only state that crepitus occurred, but also describe its behavior in a way that others can reproduce and compare.
Deepening the “observe” step: what to look for beyond “present/absent”
In a high-quality assessment, “observe” includes several sub-elements:
- Audible versus tactile: Some patients hear it clearly; others feel it as vibration. Clinicians should document whether they detected it by ear, by palpation, or both.
- Quality of the sound/sensation: “fine crackle,” “coarse grind,” “grating,” “low-frequency rumble,” etc. Even though such descriptors are subjective, they can be standardized within a clinic so that later visits can be compared.
- Location of perception: where the patient points, where the clinician palpates, and whether the sensation localizes to a bony landmark versus diffuse joint line.
- Side and comparators: assessing both symptomatic and asymptomatic sides can help determine whether the crepitus is unique to the painful joint or a generalized finding.
- Context of movement: weight-bearing versus non-weight-bearing, loaded squats versus open-chain knee extension, overhead reaching versus neutral arm elevation, etc.
The observation step is where Drf Crefito becomes most practical, because it sets up the subsequent quantification and correlation. If the observation is vague, the quantification and correlation become guesswork.
Quantify responsibly: turning subjective impressions into consistent descriptors
Clinicians often hesitate to quantify crepitus because it seems too subjective. Yet quantification is still possible through consistent documentation strategies that do not require expensive equipment.
Examples of clinically usable quantification include:
- Intensity scale: a simple mild/moderate/severe scale tied to observable criteria (e.g., “mild: only detectable by palpation; moderate: audible in quiet room; severe: audible without close attention and associated with pain”).
- Frequency during repetitions: “present in 3 out of 5 trials,” “reproducible every repetition,” or “only at the beginning of range.”
- Range phase mapping: indicating early/mid/end range is helpful, but clinicians can be more specific by using degrees or anatomical landmarks (e.g., “crepitus starts around 30° flexion, peaks at 60°, resolves near 90°”).
- Pain coupling: documenting pain as occurring before, at the same time as, or after the crepitus, and recording pain severity on a standardized scale (e.g., 0–10 NRS).
Quantification doesn’t need to be perfect; it needs to be consistent. When notes include consistent quantification, care teams can track changes over time. For instance, a clinician can later determine whether rehabilitation reduced pain but crepitus persisted, or whether both improved together—each pattern suggests different underlying mechanisms and different expectations for prognosis.
Correlate with a structured question set
The correlation step is often underestimated because it sounds like “ask more questions.” But when correlation is done systematically, it becomes a tool for narrowing differential diagnosis.
One correlation approach aligned with Drf Crefito documentation is to ask questions in a sequence that links crepitus to symptoms and mechanics:
- Timing: “Does the crackling happen before pain begins, while pain is worst, or after pain?”
- Mechanical events: “Do you feel catching, locking, or a moment where the joint won’t move smoothly?”
- Swelling pattern: “Does swelling appear later the same day, the next day, or never?”
- Stiffness profile: “How long does morning stiffness last—minutes, hours, or most of the day?”
- Functional triggers: “Is it worse with stairs, squatting, prolonged sitting, standing, or turning?”
- Activity response: “After a longer walk or workout, does it get better (warm-up) or worse (load intolerance)?”
These questions align with how evidence-based clinicians build a differential diagnosis: they evaluate whether symptoms fit inflammatory, degenerative, post-traumatic, or purely mechanical drivers. Crepitus is then interpreted through that lens.
Plan with decision thresholds: how crepitus influences management
Management decisions should rarely hinge solely on whether crepitus is present. Instead, Drf Crefito supports planning by encouraging clinicians to identify the probability that crepitus represents:
- Degenerative changes: typically more common in older patients, often with activity-related pain, joint stiffness that may improve with movement, and radiographic correlation when indicated.
- Mechanical overload or altered tracking: often linked to movement control deficits, strength imbalances, or gait mechanics.
- Inflammatory processes: less common when crepitus is the only finding, but possible when there is swelling, prolonged morning stiffness, systemic symptoms, or multiple joint involvement.
- Post-traumatic or structural injury: more likely when onset is sudden after trauma, when there is locking/catching, or when joint instability is suggested.
Even if imaging is not immediately pursued, the plan can include conservative strategies targeted to the suspected mechanism. For example, if crepitus is strongly linked to patellofemoral movement and occurs during loaded knee flexion, strengthening of hip and quadriceps control and movement retraining may be prioritized. If crepitus is paired with swelling and end-range pain, clinicians might increase focus on controlling inflammatory response and load management, and consider time-based reevaluation.
Designing clinic SOPs: making Drf Crefito reproducible across clinicians
Many care teams operate with inconsistent documentation styles. A key implementation challenge for frameworks like Drf Crefito is training and standardization: one therapist may record “crepitus,” another “cracking,” another “grinding,” and another “crepitus noted.” The SOP solution is to standardize the fields rather than the label.
A practical clinic documentation SOP could require that every crepitus note includes:
- Joint, side, and exact location (if possible)
- Audible/tactile/both
- Movement task (e.g., knee flexion/extension, squat, overhead reach)
- Range phase (early/mid/end; optionally degrees)
- Reproducibility count (e.g., present in all 5 trials)
- Pain relationship (before/same/after)
- Associated findings (effusion, tenderness, ROM loss, locking, instability)
- Functional impact and relevant history
When fields are standardized, the clinical meaning of the note remains stable even when terminology varies. This is how Drf Crefito improves communication across disciplines.
How to avoid diagnostic pitfalls: common errors when documenting crepitus
Even well-intentioned clinicians can commit diagnostic or documentation errors. A Drf Crefito-informed approach encourages awareness of these pitfalls:
- Error 1: “Crepitus = osteoarthritis.” Crepitus may occur in OA, but also in tendinopathies, post-traumatic changes, and mechanical tracking problems. Without symptoms and exam coherence, the diagnosis is not justified.
- Error 2: “Crepitus absent = no problem.” Some patients have significant pain and dysfunction without audible/tactile crepitus. The absence of crepitus should not reduce attention to other findings.
- Error 3: “Record it once, never reassess.” Crepitus characteristics may change with healing, load management, or therapy. Reassessment supports care quality and helps adjust the differential.
- Error 4: “Ignore phase and pain relationship.” The timing of crepitus relative to pain often carries mechanistic clues. End-range pain may suggest different structures than pain at mid-range.
- Error 5: “Don’t compare sides.” Without a comparator, clinicians may overinterpret incidental age-related crepitus as the driver of symptoms.
- Error 6: “Overlook red flags.” Crepitus is not a reason to delay urgent evaluation if infection, acute trauma, or systemic signs are present.
By explicitly addressing these pitfalls, teams can use Drf Crefito as a safety and quality tool rather than merely an acronym.
Joint-by-joint nuance: how Drf Crefito adapts across common regions
Crepitus occurs across many joints. However, the way clinicians assess it and what they prioritize differs by region due to anatomy and common pathologies. Below are practical examples showing how a Drf Crefito-style note can adapt while maintaining the same framework.
Knee crepitus: patellofemoral vs tibiofemoral clues
In knee assessment, clinicians commonly distinguish patellofemoral crepitus (often associated with pain during stairs, squatting, or prolonged sitting) from tibiofemoral joint-line crepitus. A Drf Crefito-informed note could include:
- Location: “patellar tendon/patellofemoral region” vs “medial/lateral joint line.”
- Movement phase: “crepitus occurs during early flexion” vs “only near terminal extension.”
- Mechanical symptoms: “no locking” versus “intermittent catching at ~45–60°.”
- Effusion: “none” vs “mild effusion after activity.”
- Functional task: sit-to-stand, descending stairs, or loaded knee flexion.
These details help determine whether the likely driver is maltracking and load control (which responds well to targeted rehab), degenerative change (where symptom management and strength/endurance are crucial), or structural injury requiring further evaluation.
Shoulder crepitus: rotator cuff and scapulothoracic interactions
Shoulder crepitus can come from multiple sources: glenohumeral joint surfaces, subacromial region, or scapulothoracic mechanics. A clinician should document:
- Movement task: overhead reach, scapular elevation/depression, internal/external rotation.
- Associated pain: crepitus with pain during a specific arc may suggest impingement-related mechanisms or rotator cuff tendon irritation.
- Scapular mechanics: dyskinesis, altered rhythm, or winging (document observed patterns).
- Instability signs: apprehension, anterior translation sensations, or history of dislocation.
In a Drf Crefito approach, the goal is to avoid oversimplifying shoulder crepitus into “arthritis.” Instead, the note should specify the movement context and whether there are accompanying functional deficits that rehab can target.
Elbow crepitus: lateral epicondyle mechanics and post-traumatic considerations
Elbow crepitus often appears in contexts involving tendon irritation, repetitive loading, or post-traumatic changes. Documentation should include:
- Elbow motion: flexion/extension at specific degrees, pronation/supination if relevant.
- Tenderness points: lateral epicondyle, radial head region, or olecranon.
- Strength/pain behavior: does pain worsen with resisted wrist extension or gripping?
- History: prior fracture, dislocation, or occupational repetitive loading.
This information helps the care team decide whether to prioritize tendon-focused rehab, mobility and mechanics training, or further evaluation if structural concerns are suspected.
Hip and spine-related “creaks”: differentiating joint crepitus from mechanical noise
Sometimes patients use “creaking” language to describe sensations that originate in hip joint structures, labrum-related issues, iliopsoas region, or even lumbar movement. A Drf Crefito note should therefore document:
- Exact pain/crepitus location: anterior groin, lateral hip, buttock, or back.
- Provocative movements: hip flexion in standing, crossing legs, rotational maneuvers, bending/lifting.
- Neuro signs: numbness, tingling, weakness (important for differential diagnosis).
Without that localization and mechanistic coherence, clinicians may misattribute symptoms. The framework helps enforce localization and correlation.
Tracking change over time: reassessment strategies for Drf Crefito
Assessment is not a single moment; it is a dynamic process. Drf Crefito supports high-quality care by emphasizing reassessment—comparing whether crepitus characteristics change in parallel with pain and function.
A reassessment plan can include:
- Repeat the same movement tests: same protocol, similar speed, similar load, and similar range.
- Re-record crepitus timing and intensity: “same phase but less intense” or “crepitus no longer audible but tactile persists.”
- Re-check pain relationship: whether pain now occurs after the crepitus rather than with it.
- Re-evaluate functional tasks: stair tolerance, sit-to-stand repetitions, overhead reaching duration.
- Reconsider differential: if symptoms improve but crepitus persists unchanged, it may represent benign mechanical noise; if symptoms worsen or crepitus pattern changes, it may signal progression.
By building this into the care pathway, clinicians transform crepitus documentation into a longitudinal monitoring tool.
Education and communication: what patients need to understand
A major clinical value of documenting crepitus correctly is communicating with patients effectively. Patients often hear “cracking” and assume it means “damage is happening right now.” In reality, crepitus can occur for multiple reasons and may not always represent active degeneration. However, if crepitus is paired with pain, swelling, and reduced function, it can reflect an underlying issue that requires attention.
Education messaging aligned with Drf Crefito can include:
- Normalizing without dismissing: “Crepitus can happen even when the issue is mild, but in your case we linked it to pain and movement changes.”
- Clarifying purpose of assessment: “We’re checking where and when it occurs to understand what structures are involved.”
- Setting expectations: “Even if the sound changes slowly, pain and function can still improve with targeted rehab.”
- Safety net: “If you develop new swelling, fever, inability to move the joint, or severe worsening after injury, we’ll escalate evaluation.”
When education is aligned with documentation, patients are more likely to adhere to treatment and perceive care as coherent and evidence-based.
Rehabilitation programming linked to Drf Crefito findings
While general conservative management was previously described, a Drf Crefito-informed approach can be more specific by linking rehabilitation emphasis to the crepitus pattern and associated symptoms.
Examples include:
- If crepitus appears with loaded flexion and is painful: clinicians may reduce provocative loading temporarily and increase controlled strengthening and mechanics retraining.
- If crepitus appears with stiffness at end range: mobility and soft tissue strategies may be prioritized, along with gradual end-range tolerance training.
- If crepitus coincides with catching/locking sensations: clinicians may adjust rehab intensity, emphasize symptom-limited mobility, and consider earlier imaging or specialist referral.
- If crepitus is present but pain is minimal: focus may shift toward function and conditioning rather than aggressive interventions.
Crucially, these adjustments should be guided by documentation: a clinician should be able to read the note and understand why certain rehab choices were made. This is one of the core practical outcomes that Drf Crefito aims to achieve.
Imaging and referral: using crepitus as a signal, not a command
Even though imaging may not always be needed, a Drf Crefito-informed note helps justify when imaging or referral is appropriate. Instead of ordering imaging because “crepitus exists,” clinicians order imaging when crepitus is part of a broader pattern that suggests a specific structural concern or when conservative management fails.
Consider imaging/referral when documentation shows:
- Red flags: fever, systemic symptoms, severe trauma, progressive neurological signs, or inability to bear weight.
- Mechanical obstruction: clear locking/catching with limited range or sudden onset after injury.
- Persistent high pain with functional decline: symptoms not responding to reasonable conservative care within an appropriate timeframe.
- Unclear mechanism despite thorough exam: when the differential remains broad due to inconsistent signs and patient reports.
When imaging is obtained, the note helps radiologists and specialists interpret what they see on imaging in context (e.g., “crepitus audible at end range with pain, localized to patellofemoral region”). This improves the likelihood that imaging results translate into clinical decisions.
Template expansion: a sample Drf Crefito documentation block
To make Drf Crefito truly operational in everyday practice, it helps to use a template structure. The following is an example of what a complete documentation block might look like for a generic joint; it can then be adapted to specific joints and local documentation systems.
Crepitus (Drf Crefito framework):
- Joint/side/location: [e.g., right knee, anterior-lateral patellofemoral region]
- Detection method: [audible/tactile/both]
- Movement task: [e.g., squat to 90°, knee extension from 90° to 0°]
- Phase of motion: [early/mid/end; optionally degrees or landmarks]
- Intensity: [mild/moderate/severe or another consistent scale]
- Reproducibility: [present in all trials / 3 of 5 trials / variable]
- Pain relationship: [crepitus precedes / coincides with / follows pain; pain timing described]
- Associated findings: [effusion yes/no; tenderness yes/no; ROM limitation; catching/locking; instability]
- Functional impact: [stairs, prolonged sitting, work tasks, sports movements]
- Clinical impression link: [mechanical overload vs inflammatory features vs post-traumatic suspicion]
- Plan and follow-up: [conservative pathway with reassessment timeframe; criteria for escalation]
This template ensures that Drf Crefito notes are more than a label—they become a structured dataset for clinical decision-making.
Expanded FAQs: advanced considerations for clinicians
9) How can clinicians differentiate benign crepitus from clinically significant pathology?
A useful principle is that benign crepitus tends to be less coupled to pain and dysfunction. Clinically significant crepitus more often appears alongside one or more of the following: persistent pain, effusion, meaningful range limitation, instability/catching, progressive symptoms, and clear mechanistic coherence with the patient’s complaint. In documentation, this means “crepitus present” is insufficient; clinicians should record pain coupling, functional impact, and associated exam signs.
10) Should clinicians always compare the crepitus to the contralateral side?
When feasible, yes—especially in joints where age-related crepitus is common. Comparing helps identify whether the crepitus is likely incidental or uniquely pronounced in the symptomatic joint. That said, some conditions can be unilateral and clearly symptomatic; comparison should not delay careful assessment when red flags exist.
11) What if crepitus is present but the patient has no pain?
In that scenario, crepitus may still be meaningful if it correlates with functional limitations, reduced performance, or other subtle findings. If symptoms are absent and exam reveals no functional impairment or concerning signs, clinicians can often proceed with patient education, monitoring, and general physical activity advice rather than aggressive interventions.
12) How should clinicians handle inconsistent crepitus across sessions?
Inconsistency does not automatically mean the finding is false; it may reflect variation in load, fatigue, movement technique, or day-to-day symptom fluctuation. A Drf Crefito approach would document the inconsistency (e.g., “crepitus not reproduced in 2 of 5 trials today”) and correlate it with factors such as activity level before the visit, current pain state, and movement speed. This improves note integrity and helps the differential remain accurate.
13) Can crepitus improve even if imaging changes do not?
Yes. Pain and function can improve due to changes in strength, mobility, movement control, and inflammation even if structural changes seen on imaging remain stable. Therefore, care teams should not interpret persistence of crepitus as failure if symptom and function outcomes improve. A longitudinal Drf Crefito note helps track these patterns objectively.
14) Does crepitus always mean “damage”?
No. Crepitus is a mechanical phenomenon that can arise from joint surfaces, cartilage mechanics, tendon friction, or movement patterns. It may be associated with degeneration in some cases, but it can also be present without ongoing tissue damage. The clinical meaning depends on symptom correlation, functional impact, and progression over time.
15) How should teams document patient-reported crepitus when they cannot feel it clinically?
If the patient reports crepitus but the clinician cannot reproduce it, documentation should reflect that accurately. For example: “Patient reports audible crackling during stairs; today crepitus not reproduced on standardized test; pain response and ROM assessed.” This maintains honesty in clinical documentation and helps guide follow-up—possibly adjusting test conditions (load, speed, position) during reassessment.
16) Is it appropriate to use standardized scales for crepitus intensity?
Yes, as long as the scale is used consistently and defined clearly within the clinic. Some clinics define intensity based on whether crepitus is audible in a quiet room versus only tactile, or based on correlation with pain. The key is that the scale should be operational and reproducible so different clinicians interpret it similarly.
Implementation challenges and practical solutions
Adopting Drf Crefito as a documentation framework may encounter real-world constraints: time limits, variable training, and inconsistent electronic health record templates. Several practical solutions can help.
- Solution 1: create a short “minimum viable” note: require fields for joint, location, audible/tactile, phase, pain relationship, associated signs, and functional impact.
- Solution 2: add prompts rather than free text: EHR checkboxes and dropdowns for phase (early/mid/end) and association (pain precedes/coincides/follows).
- Solution 3: standardize the exam protocol used by the clinic: define the movement tasks and repetition counts for common joints so that notes are comparable.
- Solution 4: train clinicians with video demonstrations: short case-based training helps align interpretation of what “audible” versus “tactile” means.
- Solution 5: audit notes for completeness: periodic review ensures that “crepitus present” notes are supplemented with the missing fields.
These solutions keep Drf Crefito from becoming another acronym that exists only on paper. Instead, it becomes a practical system for quality improvement.
Red flags and safety net expansion: making escalation criteria explicit
While red flags were already listed in general terms, clinicians often benefit from explicitly documenting safety net criteria. A Drf Crefito-informed workflow should include patient-facing escalation guidance, such as when to return urgently.
Examples of safety net language clinicians might document include:
- Post-traumatic red flags: worsening swelling, inability to bear weight, deformity, or rapidly increasing pain after injury.
- Infection/inflammatory red flags: fever, chills, severe persistent warmth over the joint, or systemic symptoms.
- Neurologic red flags: progressive numbness, weakness, saddle anesthesia, or bowel/bladder changes (depending on region and context).
- Thromboembolic concerns: in lower limb complaints where swelling and pain might not be purely musculoskeletal, clinicians should follow local protocols for evaluation.
Documenting escalation criteria supports shared decision-making and reduces the risk of delayed care.
Conclusion: using Drf Crefito to improve clinical clarity
Properly applied, Drf Crefito and Crefito-related assessment practices can raise the quality of musculoskeletal care by turning a vague report (“it cracks”) into a clear clinical observation that supports better differential thinking and more consistent follow-up. The central principle is simple and objective: document crepitus as a measurable phenomenon, then interpret it in the full clinical picture.
If you tell me the target joint (knee, elbow, shoulder, or another region) and the intended audience (clinician, student, patient education, or clinic SOP), I can tailor the workflow, FAQs, and documentation template structure accordingly.
-
1

Explore the Tranquil Bliss of Idyllic Rural Retreats
-
2
Unlock the Full Potential of Your RAM 1500: Master the Art of Efficient Towing!
-
3
Leveraging High-Interest CDs for Optimized Investment Returns
-
4
How to Take Advantage of Debt Consolidation Loans: Key Strategies
-
5
Understanding Debt Consolidation Loans: Weighing Advantages and Disadvantages